How Home Health Agencies Fax Hospital Discharge Summaries to Primary Care Doctors
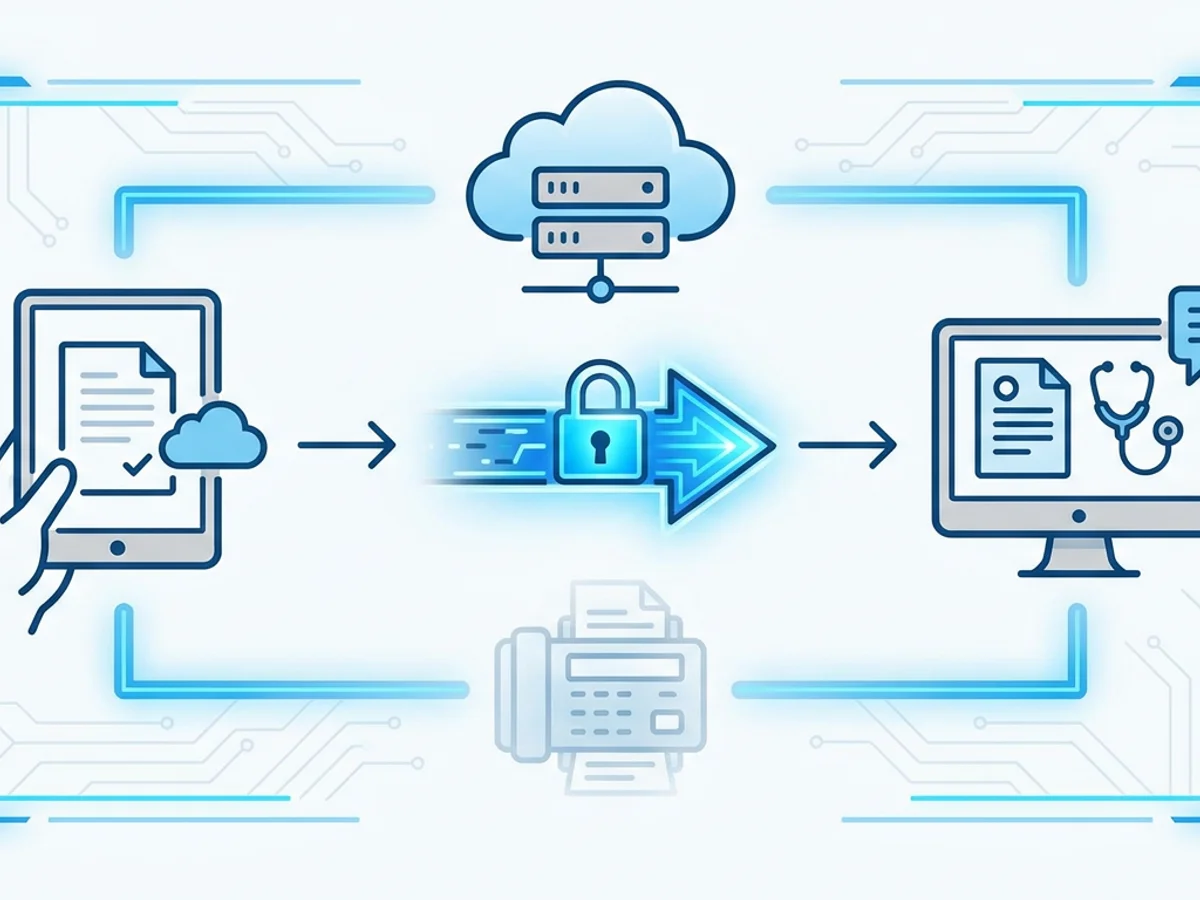
A patient has arrived home from the hospital, and the home health nurse is preparing for the first visit. The primary care office needs the discharge summary, but the agency’s copy may be buried in a referral packet, the doctor’s fax number may be outdated, and the medication list may have changed since discharge.
A successful handoff starts with more than pressing Send. The agency needs to confirm that it has the right document, identify the clinician responsible for follow-up, verify the destination, and check that the fax was delivered. If the information is urgent or incomplete, a phone call may be just as important as the fax.
Start with the discharge information you actually have
Home health agencies may receive a hospital discharge summary as part of a referral, through a care coordination process, or directly from the hospital. Sometimes the referral packet contains only a partial summary or a preliminary medication list. Before forwarding anything, check the document’s status and source.
For example, a nurse reviewing a new referral might find a discharge instruction sheet but no signed discharge summary. The instruction sheet may be useful, but it should not be labeled as the complete hospital summary. If the primary care doctor needs the full document, contact the hospital or the appropriate referral source to request it.
Check these details before preparing the fax:
- Patient identity: Match the document to the agency’s patient record using the identifiers your organization requires.
- Hospital encounter: Confirm that the summary relates to the correct admission and discharge date.
- Document status: Look for signs that it is final, preliminary, incomplete, or superseded.
- Intended recipient: Verify which primary care clinician or practice is responsible for follow-up. The name on an older record may no longer be current.
- Included information: Review whether the summary contains the discharge diagnoses, medication information, follow-up instructions, and other details relevant to the handoff.
Do not quietly edit a hospital-authored summary to resolve an apparent discrepancy. If the home health team discovers a difference between the discharge list and the medications in the patient’s home, communicate that observation separately and identify who recorded it. Follow the agency’s clinical escalation process when a discrepancy could affect patient safety.
Also check the agency’s policies and applicable requirements before sharing records. Send only the information appropriate for the care coordination purpose, and follow any organizational rules for authorizing and documenting the disclosure.
Verify the destination and prepare a useful packet
A fax number copied from an old referral or a web search is not necessarily the right destination. Practices move, consolidate, and use different numbers for different departments. Confirm the number through a trusted source, such as a current practice directory maintained by your organization or a call to the primary care office. If you call, ask which fax number should receive hospital discharge records and whether the office wants the packet addressed to a particular clinician or team.
Suppose the hospital summary names Dr. Patel, but the patient tells the visiting nurse that their primary care practice changed two months ago. Pause before sending. Confirm the current care relationship through the agency’s usual process, then verify the destination with the receiving practice. Sending a complete summary to the wrong office creates a different problem from sending it late.
A practical packet can include a cover page followed by the hospital document and any separate, relevant agency communication. Keep the cover page concise:
To: Primary care practice and clinician or care team
From: Home health agency, sender’s name, and callback number
Re: Patient identifiers required by your agency’s policy
Pages: Total pages, including the cover page
Purpose: Hospital discharge summary for continuity of care
Action requested: Review before the scheduled follow-up; call the agency about the noted medication discrepancy
Use the cover page to explain what the recipient is receiving and what, if anything, needs a response. It should not substitute for a direct call when a concern requires prompt clinical attention. Include the agency’s callback number so the practice can report missing pages, an apparent wrong recipient, or questions about the handoff.
Before sending, open each attachment and check that it is legible, oriented correctly, and complete. Confirm the page count against the packet you intend to transmit. Remove unrelated records that may have been included in a larger referral bundle. If the discharge summary is unusually long, check with the receiving office about its preferred way to receive it rather than assuming a large fax will be convenient.
Send through a browser, then check the result
If the agency has approved browser-based faxing for this workflow, staff can use BestFax.com from a phone, tablet, or computer. The service works in Safari, Chrome, Firefox, and Edge without an app download. It accepts PDF, Word, and image files and includes professional fax cover pages.
A typical workflow looks like this:
- Prepare the files. Save or otherwise make the approved discharge summary and any separate agency note available for upload. Follow your organization’s rules for handling patient records on the device being used.
- Create the cover page. Identify the receiving practice, the sender, the purpose, the total page count, and a callback number. Include patient identifiers only as required by agency policy.
- Enter the verified fax number. Compare every digit with the trusted source. A second check by another staff member may be appropriate if your agency’s procedure calls for it.
- Upload and review. Add the files, then check the recipient information, cover page, and attachments before sending.
- Send and review the receipt. Keep the delivery confirmation according to the agency’s documentation and retention rules, and record the handoff in the appropriate place in the patient record.
The service provides fax confirmation and delivery receipts. A receipt can help establish that the fax was delivered to the destination number, but it does not establish that the intended clinician read the summary, reviewed the medication list, or acted on the information. For a time-sensitive issue, contact the practice using the agency’s escalation process and document the conversation.
If delivery fails, do not assume the office received a partial packet. Check the number and the reported result, contact the practice if needed, and follow agency procedure before resending. If a fax reaches a wrong number, promptly follow the organization’s incident-response process rather than simply sending another copy to the correct office.
Decide if the service fits the agency’s workflow
Browser access can be useful when an authorized staff member needs to send a document away from a physical fax machine. It does not, by itself, resolve the organization’s privacy, contracting, or clinical workflow requirements.
The service uses TLS encryption for fax transmissions. It does not offer a BAA or a healthcare-specific compliance certification. An agency should have its privacy, security, and legal teams assess those limitations and its own obligations before using the service for patient records. If the organization requires a BAA or a certification the service does not provide, staff should use an approved alternative.
The device matters too. A home health employee using a tablet during a visit should follow agency rules for device access, local file storage, screen visibility, and disposal of temporary copies. Avoid displaying a discharge summary where household visitors or other unintended viewers can see it. If a document is downloaded to upload it, handle that local copy according to the organization’s procedures.
For budgeting, the listed options are $4.95 one-time per fax or a $10 monthly subscription. Compare those costs with the agency’s anticipated fax volume and its internal approval requirements. A low-volume workflow may call for a different purchasing decision from a team that sends records regularly; either way, confirm that the service meets the organization’s requirements before transmitting patient information.
The final step is to close the loop. Note what was sent, when it was sent, the verified destination, and the delivery result in the designated record. If the primary care office was asked to act on a discrepancy, assign responsibility for follow-up rather than treating the receipt as the end of the process.
Get started at BestFax.com.
Related Posts
How Ambulance Services Fax PCS Forms for Medicare Nonemergency Transport
Learn when Medicare nonemergency ambulance trips may require a PCS, how to fax a request, and what to check when the signed form returns.

How Dental Offices Fax Oral Surgery Referrals With X-Rays and Medical Histories
Learn how to prepare and fax an oral surgery referral with medical history and X-rays, check image quality, and confirm delivery.
How Teleradiology Groups Fax Wet Reads to ERs Without STAT Delays
Practical guidance for teleradiology teams that need to fax ER wet reads quickly, with clear routing, cover pages, receipts, and fewer STAT delays.